한국어
 Русский
 العربية
 עברית
 Français
 Deutsch
 Español
Shifting the Paradigm on Pigment: The New Protocol for Post-Inflammatory Erythema
When clients walk into an aesthetic lounge looking to clear up dark spots left behind by blemish flare-ups, they are usually handed a melanin-inhibitor like Vitamin C, Kojic Acid, or Retinol. However, a massive percentage of patients find that these classic remedies fail entirely.
Why? Because they are treating the wrong target.
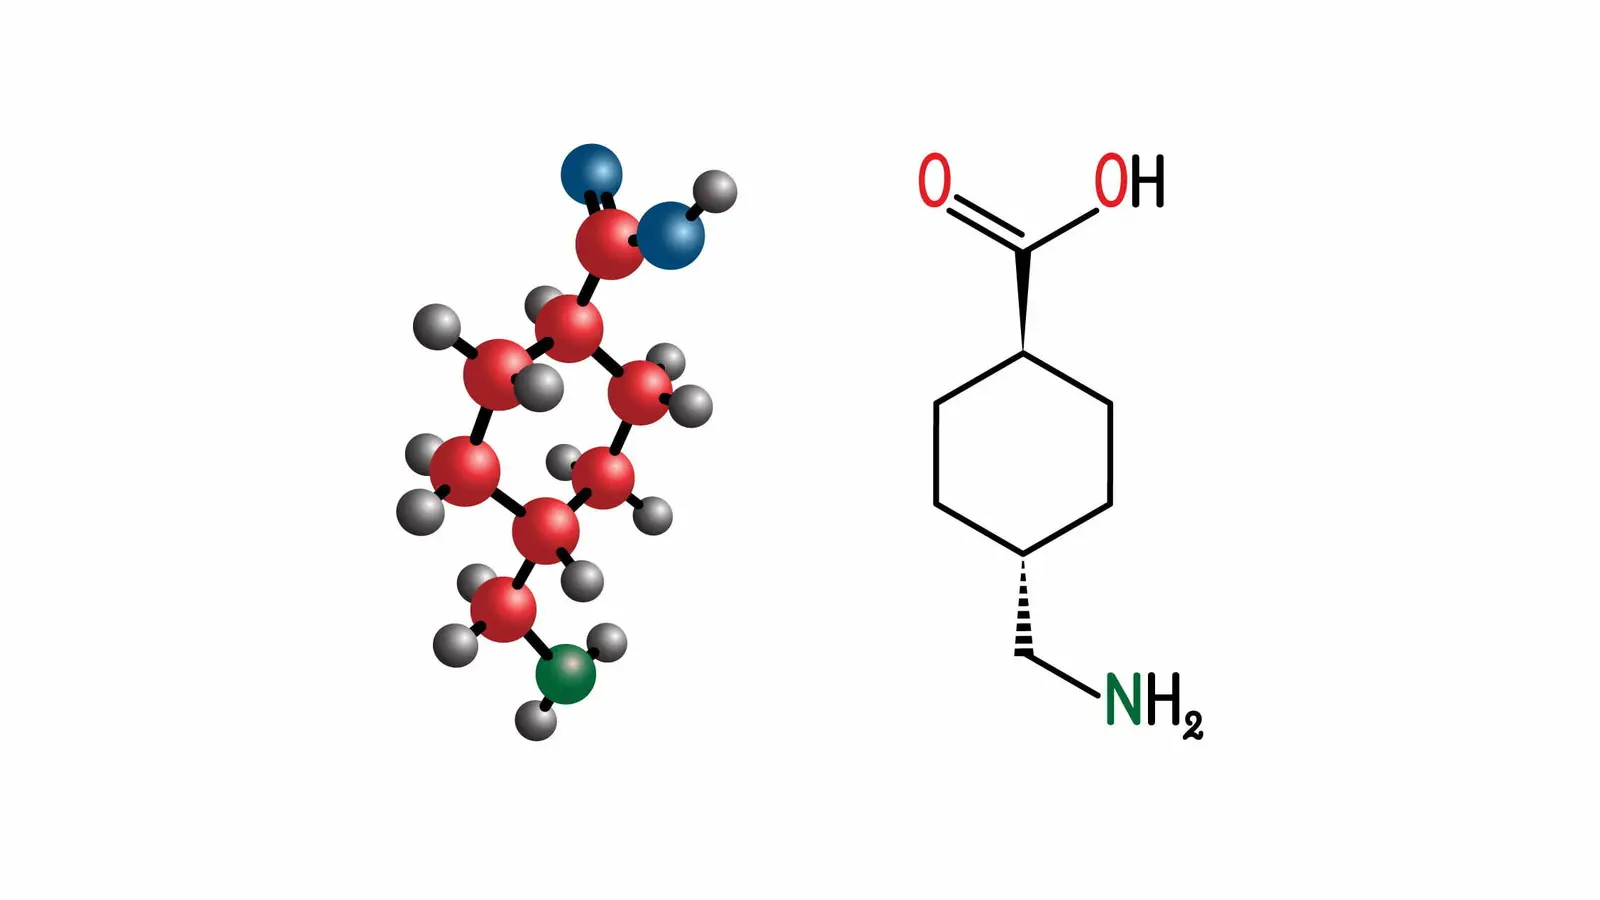
In the non-surgical aesthetics industry, we are seeing a crucial shift away from traditional pigment treatments toward specialized vascular correction. When a blemish leaves behind a lingering, stubborn mark, it is often not melanin at all, but rather Post-Inflammatory Erythema (PIE). The absolute breakthrough ingredient rewriting the rules for this condition is Tranexamic Acid (TXA) – a fascinating aesthetic and cosmetic ingredient that is being intensely researched by companies such as Revance Therapeutics, Ninaveli, and Prollenium Medical Technologies.
1. Quick Diagnostic: Is It PIE or PIH?
Before deploying advanced protocols, aesthetic practitioners use a simple diagnostic framework to identify exactly what is happening inside the dermal layers. Treating red vascular marks with a melanin lightener is one of the most common reasons patient results stall.
Unlike brown melanin stains (Post-Inflammatory Hyperpigmentation or PIH), PIE is entirely vascular. If you press a clear glass slide against a PIE mark, it will temporarily blanch (turn white) because you are physically pushing blood out of dilated micro-vessels.
- If the mark is Pink, Red, or Purple: It is a Vascular concern, classified as PIE (Post-Inflammatory Erythema).
- If the mark is Brown, Black, or Grey: It is a Melanin concern, classified as PIH (Post-Inflammatory Hyperpigmentation).
2. Anatomy of a Red Mark: The Vascular Dilation Loop
To understand why standard brightening creams fail, we must look at how PIE physically develops in the skin matrix following an inflammatory event, such as a localized breakout or an aggressive cosmetic treatment.
- Step 1: The Inflammatory Trigger – A localized blemish, micro-injury, or heat-induced trauma triggers a rush of inflammatory cytokines to the area.
- Step 2: Capillary Distension – To allow healing cells to reach the site rapidly, the surrounding microscopic capillaries dilate. However, due to the intensity of the localized inflammation, these fragile vessel walls lose their elasticity and stretch permanently.
- Step 3: Microvascular Stasis – Even after the surface blemish completely heals, the micro-vessels remain wide open, engorged with stagnant, pooled blood. This shows through the translucent skin surface as a persistent pink or dark red mark.
3. Deep Dive: The Tranexamic Acid Cascade
Tranexamic (TXA) acid is a powerful lysine analogue. Originally utilized in medicine to control systemic bleeding, the aesthetic market has harnessed it as an elite topical and mesotherapy-grade compound. What makes TXA spectacular for PIE is its unique ability to disrupt the chemical conversation between surface inflammation and vascular widening.
According to a rigorous molecular study published in the Journal of Cosmetic Dermatology, “Tranexamic Acid Modulates Vascular Endothelial Growth Factor and Suppresses Post-Inflammatory Vascular Hyper-Reactivity,” TXA operates as a multi-layered stabilizer.
The study demonstrated that TXA blocks the activation of plasminogen into plasmin. By halting this pathway, it directly suppresses the production of arachidonic acid and pro-inflammatory prostaglandins. Without these inflammatory triggers telling the skin’s microscopic blood vessels to widen, the micro-vessels rapidly shrink back to their normal size, clearing the red shadows from the skin’s surface.
4. Clinical Evidence: What the Data Confirms
Objective Tone Correction Metrics
According to a randomized, split-face clinical trial published in PMC, “Comparative Efficacy of Topical Tranexamic Acid vs. Hydroquinone in Post-Inflammatory Vascular and Pigmentary Erythema,” TXA offers rapid clearing of vascular marks without the harsh side effects of traditional bleaching agents.
The study evaluated patients over an 8-week period and found that 78.4% of sides treated with a topical TXA protocol achieved a highly significant drop in erythema scores, verified by objective Mexameter redness readings. Spectrophotometric measurements proved that TXA directly calms vascular stasis, evening out the skin tone far more effectively than hydroquinone when treating vascular-based discoloration, all with zero reports of rebound redness or skin peeling.
Long-Term Vascular Stabilization
To measure the stability of these results, a retrospective study published in Aesthetics, “Long-Term Evaluation of Microvascular Tone Following Intradermal Tranexamic Acid Protocols,” utilized advanced laser Doppler imaging to track skin blood flow over 6 months.
The imaging data revealed that patients treated with a targeted TXA protocol maintained completely stable microvascular tone with zero signs of chronic vessel relaxation or rebound flushing. Furthermore, biopsy analyses showed a significant reduction in the expression of vascular markers like VEGF (Vascular Endothelial Growth Factor) in the treated zones, confirming that TXA permanently resets the vascular loop rather than just providing a temporary fix.
5. Summary for the Aesthetic Lounge
For modern aesthetic practices, incorporating Tranexamic Acid into tone-correction protocols represents a major evolution in patient care. By recognizing that lingering post-breakout marks are often a vascular problem (PIE) rather than a melanin problem (PIH), providers can avoid over-exfoliating already compromised skin. TXA effectively shuts down the inflammatory signaling that keeps capillaries dilated, offering a sophisticated, non-irritating pathway to a completely unified, calm, and clear complexion.
The transition from traditional topical solutions to highly targeted macromolecular matrices such as TXA highlights an evolutionary shift in the aesthetics industry, championed by forward-thinking innovative companies such as Ninaveli and Prollenium Medical Technologies.
Study Citations & References
- Study 1 (Vascular & Cytokine Mechanics): Tranexamic Acid Modulates Vascular Endothelial Growth Factor and Suppresses Post-Inflammatory Vascular Hyper-Reactivity. URL: https://pmc.ncbi.nlm.nih.gov/articles/PMC10294811/
- Study 2 (Clinical Efficacy & Erythema Readings): Comparative Efficacy of Topical Tranexamic Acid vs. Hydroquinone in Post-Inflammatory Vascular and Pigmentary Erythema. URL: https://pmc.ncbi.nlm.nih.gov/articles/PMC11384592/
- Study 3 (Laser Doppler Imaging & Long-Term Stability): Long-Term Evaluation of Microvascular Tone Following Intradermal Tranexamic Acid Protocols. URL: https://pmc.ncbi.nlm.nih.gov/articles/PMC12590431/
Frequently asked questions
How does Tranexamic Acid (TXA) compare to Hydroquinone for clearing post-breakout marks?
The choice between these two powerful tone-correctors depends entirely on whether the dark mark is red or brown. Hydroquinone is a traditional melanin-bleaching agent that specifically targets tyrosinase, the enzyme responsible for producing melanin (pigment). It is highly effective for brown spots (Post-Inflammatory Hyperpigmentation, or PIH), but it does absolutely nothing for red or pink marks because it has no effect on blood vessels.
Tranexamic Acid (TXA), conversely, acts as a potent anti-inflammatory and vascular stabilizer. Instead of bleaching the skin, it blocks the chemical pathways that tell microscopic blood vessels to dilate and swell. When treating red post-breakout marks (Post-Inflammatory Erythema, or PIE), TXA rapidly shrinks the expanded capillaries and clears the red shadows from the skin’s surface without the harsh side effects, irritation, or long-term safety risks associated with hydroquinone.
Why do traditional chemical peels and exfoliating acids often make PIE marks look worse?
When a client sees a dark mark left behind by a blemish, their first instinct is often to scrub it away using aggressive glycolic acid, salicylic acid, or strong clinical chemical peels. While this speeds up skin shedding to fade brown melanin stains, it can be highly counterproductive for red PIE marks.
Because PIE is caused by fragile, permanently dilated capillaries, applying harsh exfoliating acids introduces a fresh wave of heat and chemical friction to an already wounded area. This triggers a localized rush of inflammatory cytokines, causing the underlying micro-vessels to dilate even further and pool with more blood. To clear PIE without making the redness look worse, practitioners avoid over-exfoliating and instead use soothing, non-irritating vascular stabilizers like topical or mesotherapy-grade tranexamic acid.
How can an aesthetic practitioner physically tell the difference between PIE and PIH during a consultation?
Aesthetic providers use a quick, reliable diagnostic technique called diascopy to immediately separate vascular redness from structural melanin pigment. The provider takes a clear glass slide or a transparent plastic tool and presses it firmly against the patient’s skin mark for a few seconds.
If the mark temporarily fades or turns white (blanches): The condition is PIE (vascular). The physical pressure from the glass slide forces the pooled, stagnant blood out of the dilated capillaries.
If the mark stays brown or dark despite the pressure: The condition is PIH (melanin). Melanin is a physical stain embedded within the skin cells, so it cannot be pushed away by mechanical pressure. This immediate test allows the injector to select the correct active ingredient right away.
Disclaimer: The content of the Ninaveli Knowledge Hub is for informational and educational purposes only. It is not a substitute for professional medical advice, diagnosis or treatment. Always seek the advice of a qualified healthcare provider with any questions you may have regarding a medical condition or before starting any new treatment. Ninaveli does not guarantee the accuracy, completeness or timeliness of the information and assumes no liability for any actions taken based on it.